BPC-157 and TB-500 are increasingly promoted for tendon, ligament, and muscle healing. The claims are moving faster than the human evidence.
A patient with an injured tendon no longer needs to search far to find BPC-157. Online clinics and wellness practices describe it as a way to accelerate healing. TB-500 is promoted in much the same way. The appeal is obvious. Orthopaedic recovery is slow, and a treatment that could shorten it would be valuable.
Both are peptides, which are short chains of amino acids, the same basic building blocks that make up proteins. BPC stands for body protection compound, the research label given to BPC-157. TB refers to thymosin beta; TB-500 is a laboratory-made peptide related to thymosin beta-4, a protein involved in cell movement and tissue repair. The numbers are simply part of the compound names. They do not indicate the dose or strength.
But what does the evidence actually show?
The central problem is the gap between an encouraging early result and an outcome that matters to a patient.
Why Early Results Can Be Misleading
Many supplements are promoted before researchers have shown that they help patients. Early studies may find a change in a laboratory test, a scan, or an animal model. That can be encouraging, but it does not prove that people heal faster, have less pain, or become stronger.
The final step is where the evidence often breaks down. In one randomized study, collagen peptides increased Achilles tendon size in healthy men but did not provide additional improvement in tendon stiffness or strength.The tendon looked different, but it did not function better.
That distinction matters. A larger tendon, a higher collagen marker, or a favorable animal study may be scientifically interesting. It is not the same as showing that an injured patient heals faster or returns to activity sooner.
What Do We Know About BPC-157?
Cell and animal studies suggest that BPC-157 may influence tissue repair. That makes it a reasonable subject for further research. It does not establish that it works in people. A 2025 review found 36 reports. Thirty-five were laboratory or animal studies, and only one involved patients.
That one patient study looked back at 16 people treated for different types of knee pain at a single private clinic. Everyone received an injection, so there was no untreated group for comparison. The patients were not randomly assigned, and the study did not use a standard pain or function score or repeat imaging. It may justify further research, but it cannot tell us whether the treatment worked.
The human safety evidence is also extremely limited. A small pilot study administered intravenous BPC-157 to two people without a reported adverse event. Two participants and short follow-up do not establish safety, particularly for the subcutaneous and other routes commonly advertised.
The accurate conclusion is not that BPC-157 is unsafe. It is that its safety and effectiveness for musculoskeletal use remain unknown.
What About TB-500?
TB-500 is related to thymosin beta-4, a naturally occurring peptide involved in tissue repair. Researchers understand more about how thymosin beta-4 may act in the body than they do about BPC-157. It has also undergone an early human safety trial. In that study, 40 healthy volunteers received intravenous thymosin beta-4 or a placebo, and no side effect was serious enough to stop the dosing.
That is useful safety information, but it does not answer the orthopaedic question. The study lasted 14 days, involved healthy volunteers, and did not measure tendon, ligament, muscle, or bone healing. Neither BPC-157 nor TB-500 currently has convincing human evidence showing improved musculoskeletal recovery.
Availability Is Not the Same as Approval
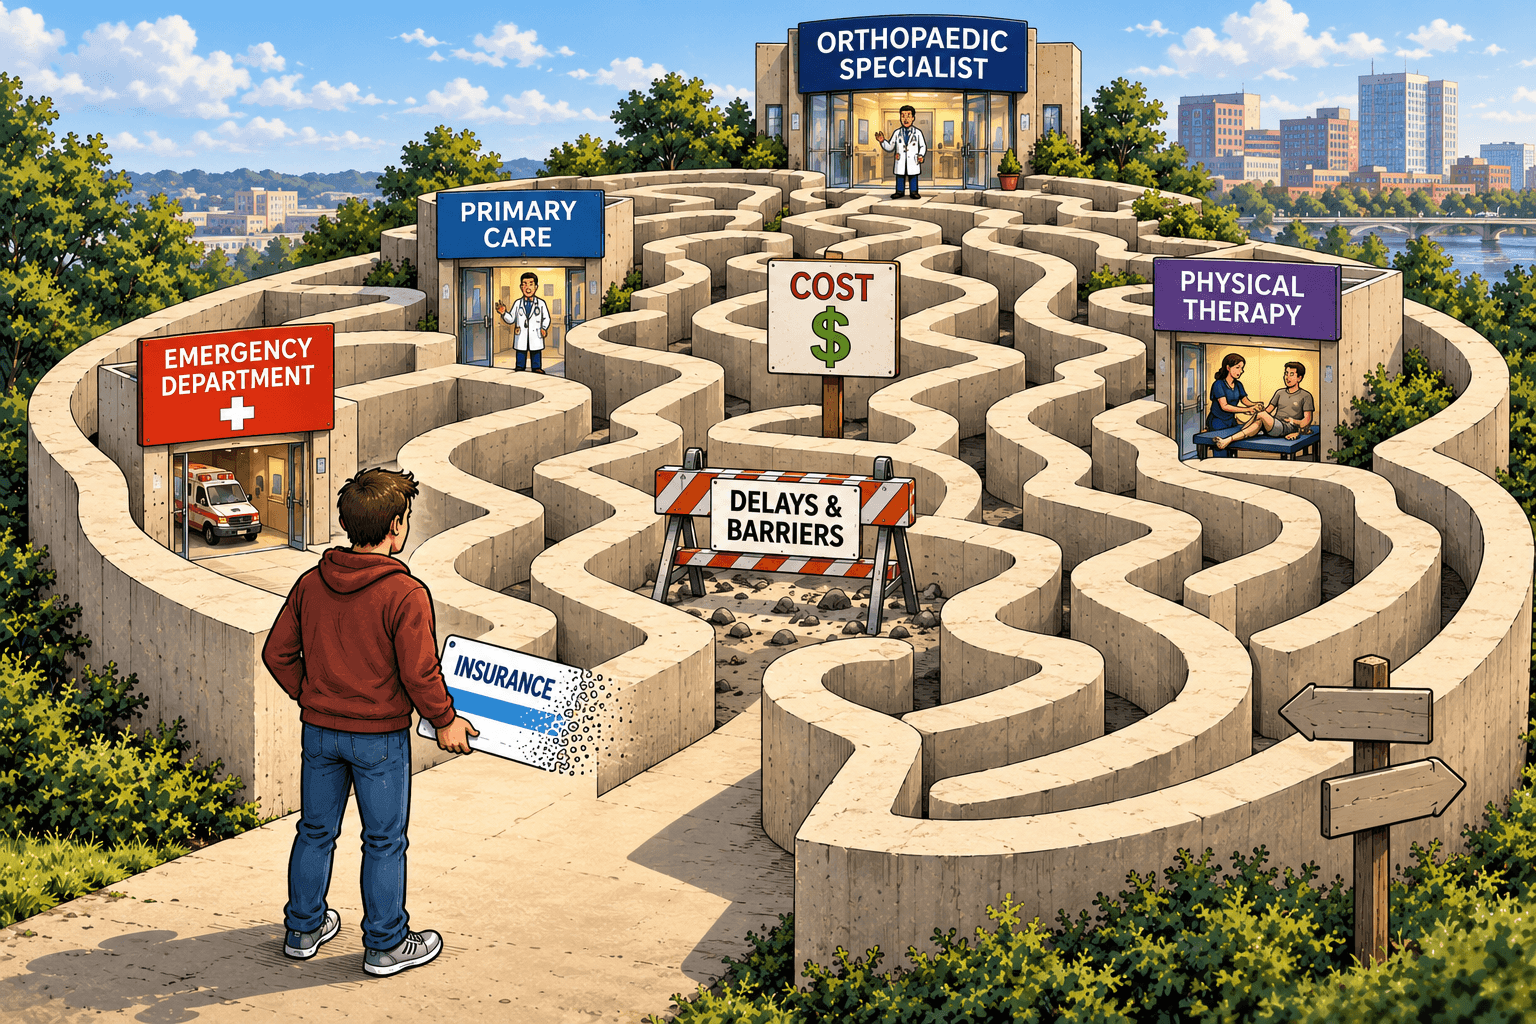
Patients may assume that receiving a peptide through a clinic or a pharmacy that custom-mixes medications means it has undergone the same review as an approved drug. It has not. In July 2026, the US Food and Drug Administration reviewed BPC-157 for possible use in compounding. FDA staff cited limited safety information and concerns about whether the product could contain impurities or trigger an unwanted immune reaction
An FDA advisory committee narrowly recommended allowing BPC-157 for compounding for ulcerative colitis. That recommendation was advisory, concerned a gastrointestinal indication, and did not validate its use for tendonitis or other orthopaedic conditions.
Competitive athletes face an additional issue. The World Anti-Doping Agency prohibits BPC-157, TB-500, and thymosin beta-4 derivatives at all times, both in and out of competition.
How Should We Discuss Peptides With Patients?
A useful discussion about emerging treatments separates four questions:
- Is there a reasonable explanation for how it might work?
- Has it improved pain, healing, strength, or recovery in a well-designed human study?
- Do we know that the product is made consistently and has been adequately reviewed?
- What are the potential risks and side effects?
For BPC-157 and TB-500, the answer to the first question may be yes. The other three remain unresolved.
That does not mean these peptides will never prove useful. Better trials may eventually identify a role for them. Until then, presenting them as established treatments goes beyond the evidence. In orthopaedics, the endpoint that matters is not whether a marker changes. It is whether the patient heals faster, becomes stronger, returns sooner, or avoids another operation. For peptides, that evidence has not yet arrived.
References
- Jerger S, Zügel M, von Wittich R, et al. Specific collagen peptides increase Achilles tendon cross-sectional area in combination with resistance training. Scand J Med Sci Sports. 2022;32(7):1131-1141. doi:10.1111/sms.14164
- Vasireddi N, et al. Emerging use of BPC-157 in orthopaedic sports medicine: a systematic review. HSS J. 2025;21(4):485-495. doi:10.1177/15563316251355551
- Ruff D, Crockford D, Girardi G, Zhang Y. A randomized, placebo-controlled, single and multiple dose study of intravenous thymosin beta-4 in healthy volunteers. Ann N Y Acad Sci. 2010;1194:223-229. doi:10.1111/j.1749-6632.2010.05474.x
- US Food and Drug Administration. BPC-157-related bulk drug substances: Pharmacy Compounding Advisory Committee briefing materials. July 23, 2026. Accessed September 10, 2026.
- World Anti-Doping Agency. The 2026 Prohibited List. Effective January 1, 2026. Accessed September 10, 2026.
About the Author
Michael Simon, MD, is a PGY-5 orthopaedic surgery resident in the Rutgers Health/Robert Wood Johnson Medical School Program. He graduated from Rutgers Robert Wood Johnson Medical School in 2022